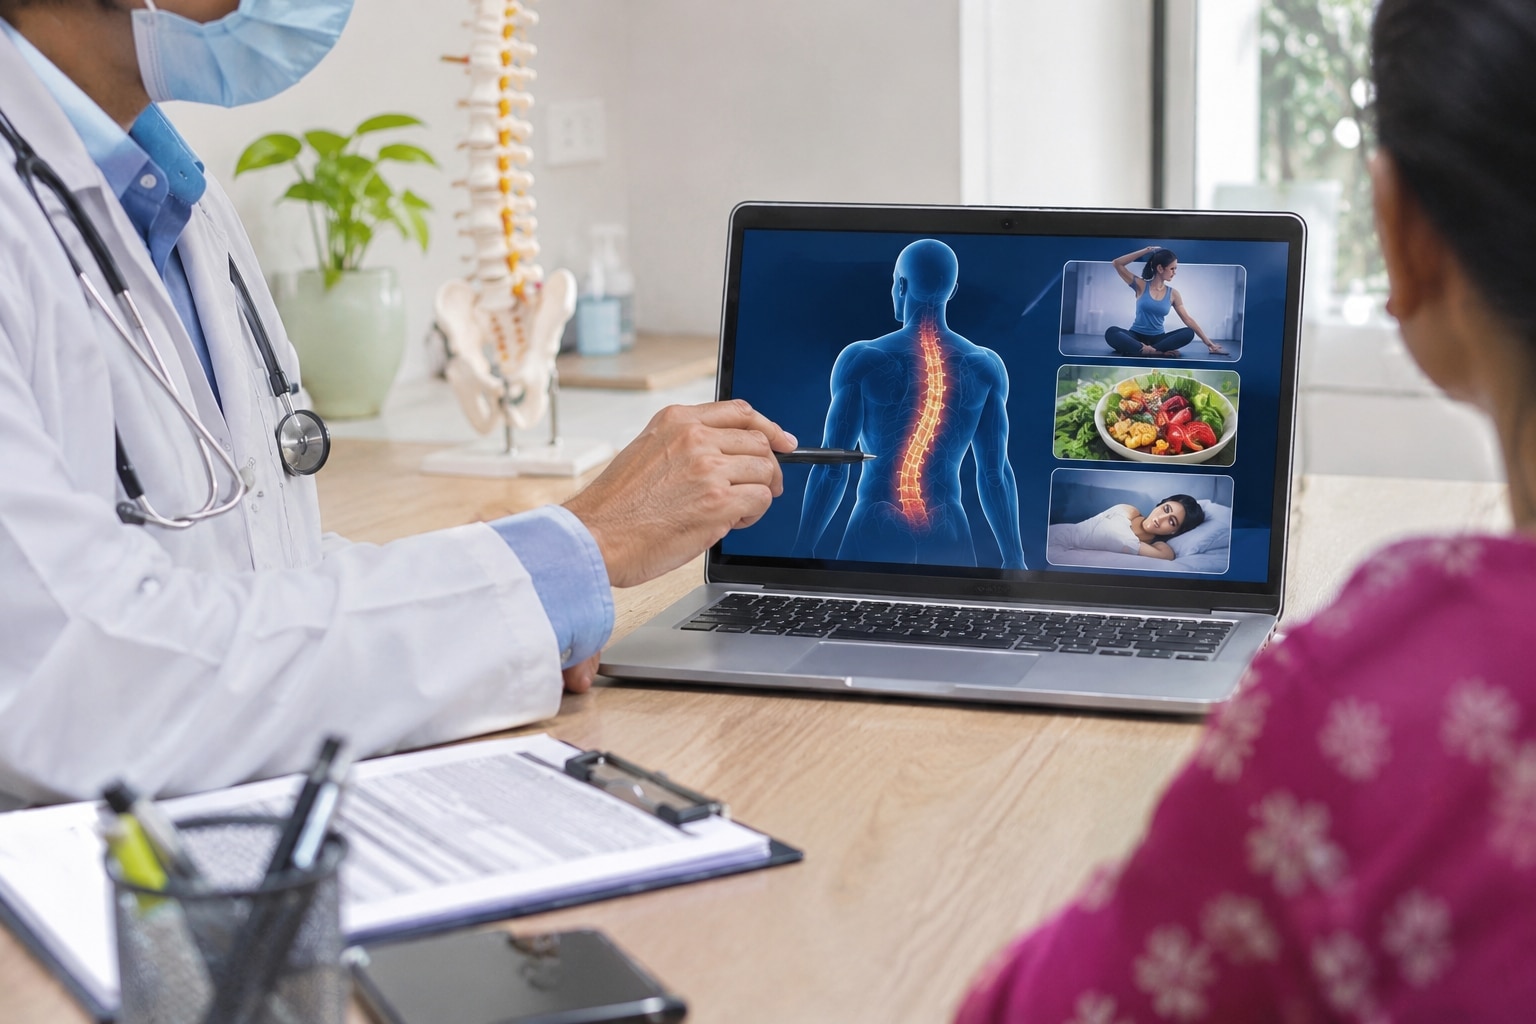


Uneven shoulders, a rotated rib cage or recurring back pain does not tell you whether you have a structural scoliosis, a pelvic imbalance or a movement habit. By the end, you will know which assessments confirm the diagnosis, which treatment paths fit a growing or mature skeleton, and how to judge whether care is improving function rather than only changing your appearance for a few minutes.
Key takeaways
- A Cobb angle of 10° or more confirms scoliosis on a standing full-spine X-ray.
- Uneven shoulders alone do not prove a structural spinal curve.
- Treatment choices include observation, exercise, bracing, and surgical consultation.
- Track improvement through function, symptoms, posture control, and curve monitoring.
What Spinal Alignment Means When Your Posture Looks Uneven
A lasting spinal curve is not the same as shoulders that sit unevenly. Structural scoliosis combines a sideways spinal curve with rotation of the vertebrae and ribs; a standing full-spine X-ray confirms it when the Cobb angle measures at least 10°.
A useful SpinalAlignment check asks whether the shape remains when you change position, relax, or follow a correction cue.
Clues that help separate the causes include:
- Ordinary poor posture often changes when you sit upright, shift position, or receive a clear movement cue. It does not create a fixed vertebral curve on X-ray.
- Pelvic asymmetry can tilt the lower spine because of leg-length difference, hip position, or muscle imbalance. Recheck the spine after assessing the pelvis rather than labelling every tilt as scoliosis.
- A temporary movement pattern appears with fatigue, guarding, pain, or a new activity and may disappear after rest. It describes how you move at that moment, not necessarily your bone structure.
- Structural scoliosis deserves assessment when rib prominence, waist asymmetry, or shoulder height remains uneven during forward bending and standing.
Massage, manual therapy, or generic posture drills can ease symptoms and briefly improve appearance, but that visual change does not prove that a structural curve has changed. A young adult also needs assessment for a curve that began in adolescence, adult degenerative change, vertebral differences, or pain-related guarding before choosing ScoliosisTreatment.
The Examinations That Confirm Scoliosis and Identify Risk
A young adult has radiographic scoliosis when a standing spinal X-ray shows a lateral curve with a Cobb angle of at least 10 degrees. The examination must establish whether that curve is structural rather than a temporary posture caused by pelvic tilt, leg-length difference, pain or muscle spasm.
The clinician checks shoulder and pelvic level, rib prominence and trunk shift during the Adam forward-bend test, then measures rotation with a scoliometer. Strength, reflexes, sensation, gait, pain distribution and breathing tolerance add risk information; pain intensity alone does not predict progression.
| Finding or result | What it helps determine | Why it matters |
|---|---|---|
| Standing full-spine X-ray | Cobb angle, curve location, vertebral rotation and balance | Confirms scoliosis and provides a baseline for comparison |
| Risser sign or other skeletal-maturity assessment | Remaining growth potential | A curve in an immature skeleton has greater progression risk |
| Serial X-rays | Documented change in Cobb angle or alignment | Progression matters more than a single photograph or painful day |
A mature curve that looks straighter during exercise has not necessarily changed structurally. Before exercise-based ScoliosisTreatment, seek medical assessment for:
- New or progressive weakness, numbness, gait change or loss of coordination
- Saddle-area numbness or new bladder or bowel dysfunction
- Severe unremitting pain, night pain, fever, unexplained weight loss or major trauma
- Rapidly increasing asymmetry or breathing difficulty
A clinician may order MRI for neurologic findings, unusual pain, rapid progression or an atypical curve, to examine the spinal cord, discs and other soft tissues.
Choosing Between Observation, Exercise, Bracing and Surgical Consultation
Skeletal maturity changes the purpose of treatment: a growing spine may still be influenced by bracing, while a mature spine is managed mainly for function, symptoms and control rather than permanent curve correction.
| Option | Still growing | Skeleton mature |
|---|---|---|
| Observation | Monitor the Cobb angle, symptoms and growth at scheduled reviews. A progressing curve needs action. | Observe stable curves when pain, function and neurological findings are reassuring. |
| Exercise | Build strength, breathing capacity, balance and active SpinalAlignment; exercise complements, rather than replaces, prescribed bracing. | Use exercise-based ScoliosisTreatment for three-dimensional postural control, trunk and hip strength, conditioning and confidence. Do not promise a straightened curve. |
| Bracing | Consider a specialist-fitted brace for a selected moderate curve with substantial growth remaining. Fit and wearing time matter. | Do not use a brace as routine curve correction. Short-term support or pain control can be considered, but prolonged reliance may hinder active rehabilitation. |
| Surgical consultation | Seek specialist review for substantial progression, severe deformity, respiratory impact or neurological findings. | Discuss consultation for a large or worsening curve, disabling pain, major imbalance or neurological compromise; surgery is not the automatic next step. |
A mature young adult still needs the correct diagnosis before choosing care. Adult idiopathic scoliosis, degenerative change, leg-length or pelvic asymmetry, congenital vertebral differences and pain-related guarding require different plans.
Night pain, weakness, numbness, gait changes, bowel or bladder symptoms, or inflammatory clues such as morning stiffness, alternating buttock pain, psoriasis or eye inflammation require medical assessment before exercise-based care.
How Exercise-Based Scoliosis Care Is Delivered in Pune
An exercise-based plan starts with a baseline, not a generic posture routine. The clinician records pain location, breathing or endurance, trunk and hip strength, neurological findings, walking and lifting tolerance, and a disability or quality-of-life score. Standing photographs can show change in control, but they do not prove that the Cobb angle has changed.
A practical SpineCareInPune programme usually follows this sequence:
- Learn a specific three-dimensional self-correction for your curve, using visual, tactile or breathing cues.
- Practise that position during simple movements such as sitting, walking, reaching and lifting.
- Build trunk, hip and shoulder strength without losing the corrected position.
- Increase repetitions, resistance or task difficulty only when control remains consistent.
- Recheck symptoms and function at planned intervals rather than judging progress after one session.
The useful test is not whether an exercise makes you tired. It is whether you can hold better SpinalAlignment, move with less compensation, and repeat the task with equal or improved control.
Reduced pain spread, longer walking or lifting tolerance, steadier balance and improved strength are stronger evidence than a temporarily straighter stance in a mirror.
Mild muscle effort can be expected; sharp pain, spreading symptoms, numbness, weakness or worsening function is a stop signal. Pro Active Clinic should adapt the programme to those findings rather than treating soreness as proof that the exercise is working.
Morning stiffness that improves with movement, alternating buttock pain, psoriasis, bowel symptoms or eye inflammation needs medical assessment for inflammatory spinal disease before assuming scoliosis explains everything.
Related service
Scoliosis and Postural Care Scoliosis Care for Young Adults At Pro Active Clinic, we provide scoliosis-focused care for young adults with an abnormal sideways curvature of the spine. View service → |
What Improvement Can Realistically Mean Over Time
A straighter photograph does not prove that an established structural curve has reduced. ScoliosisTreatment for a skeletally mature young adult aims more realistically at three-dimensional postural control, trunk and hip strength, movement confidence, conditioning and symptom management.
Keep exercising and participating in sport when symptoms allow; adjust load, range and progression rather than imposing blanket restrictions.
| Outcome | What to record | What improvement means |
|---|---|---|
| Pain and symptoms | Intensity, location, frequency and triggers | Fewer flares, less referred pain or better recovery |
| Function | Walking, sitting, lifting and training tolerance | More activity with less compensation or fatigue |
| Control and strength | Balance, trunk endurance, hip strength and movement quality | Smoother alignment under load, not merely muscle soreness |
| Curve and health | Standing Cobb angle, neurological findings, breathing or endurance | Stable imaging and normal findings; a photo alone is insufficient |
A SpineCareInPune plan should use the same measures at each review. Curve size, maturity, pattern and documented change matter more for progression risk than pain intensity; scoliosis can be painless, while pain can come from discs, facet joints or overloaded muscles.
Reassess or escalate the plan when:
- Function, strength or symptoms fail to improve after the agreed exercise period.
- New numbness, weakness, gait change, bowel or bladder symptoms, breathing difficulty, severe pain or night pain appears.
- Imaging shows progression, or pain includes prolonged morning stiffness, alternating buttock pain, psoriasis, inflammatory bowel disease or eye inflammation; seek medical or rheumatology assessment.
Frequently asked questions
What does spinal alignment mean when posture looks uneven?
Structural scoliosis combines a sideways spinal curve with vertebral and rib rotation. Uneven shoulders alone do not confirm scoliosis; a standing full-spine X-ray measures the curve using the Cobb angle.
Which examinations confirm scoliosis and identify risk?
A clinician examines posture, shoulder and pelvic level, spinal movement, neurological function, and leg-length differences. A standing full-spine X-ray confirms the curve and provides the Cobb angle for monitoring.
How do you choose between observation, exercise, bracing, and surgical consultation?
The choice depends on the Cobb angle, symptoms, curve progression, skeletal maturity, balance, and neurological findings. Smaller stable curves may need monitoring and exercise, while progression or significant symptoms require specialist review.
How is exercise-based scoliosis care delivered in Pune?
Care starts with an assessment of alignment, movement, strength, breathing, and daily activities. A programme then uses supervised, progressive exercises with practical guidance for posture, training, and symptom management.
What can improvement realistically mean over time?
Improvement can mean better movement control, endurance, balance, comfort, breathing mechanics, or confidence in daily and sporting activities. Exercise does not guarantee that a structural curve will straighten.